

Primary Care Billing Services
Primary care billing services for family medicine, internal medicine, and general practice. Accurate E/M coding, preventive care billing.
What Primary Care Billing Should Capture
Primary care revenue depends on capturing everything delivered during an encounter, not just the visit itself. Chronic care management, transitional care and preventive services are frequently documented but never billed.
- Visit levels selected on documented decision making or time
- Chronic care and transitional services captured where eligible
- Preventive and problem-focused care separated when both occur
- Quality reporting aligned with the billing workflow
Primary Care Billing Services Explained
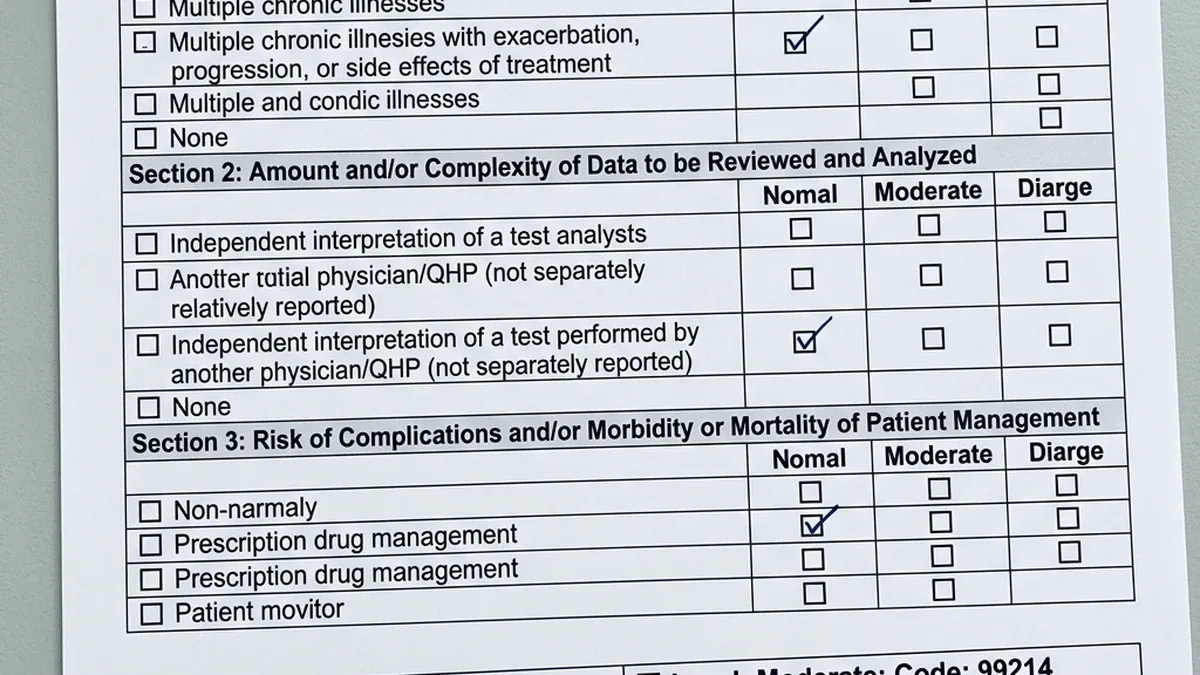
Primary care billing covers the full range of E/M coding services, preventive care, chronic care management, and annual wellness visits. Current E/M guidelines effective since 2021 changed how office visit levels are determined, the AMA replaced the element-counting methodology with Medical Decision Making or total physician time as the primary level-selection criteria. Primary care delivered in a rural health clinic is paid on an encounter rate instead, which is covered under rural health clinic billing.
Medsure RCS manages primary care medical billing services for family medicine, internal medicine, and general practice providers in Florida. We apply current AMA E/M guidelines correctly, handle electronic claims submission, bill chronic care management programs, and ensure preventive care and annual wellness visit billing is accurate across Medicare and commercial payers. Primary care is part of our specialty medical billing program. Most established patient visits land at 99213 or 99214, and the split between those two drives a large share of primary care revenue.
How It Works: Step by Step
E/M Level Determination
Visit level is determined by Medical Decision Making complexity or total physician time documented in the note, per 2024 AMA E/M guidelines.
Preventive and Problem-Based Separation
Visits combining preventive care and problem-based care are billed with correct code pairing and modifier 25 on the E/M when a significant, separately identifiable problem-based service is provided.
Chronic Care Management Enrollment
CCM-eligible patients are enrolled, and monthly CCM claims (99490-99491) are submitted with documented care plan, care coordination minutes, and clinical staff time.
Wellness Visit Billing
Medicare Annual Wellness Visits (G0438, G0439) and IPPE (G0402) are billed separately from routine problem-based E/M visits with correct documentation of covered wellness visit elements.
Why This Matters for Your Revenue Cycle
Current E/M guideline compliance and MDM documentation accuracy drive first-pass acceptance above 95%.
Every eligible CCM patient is enrolled, documented, and billed monthly with correct care plan requirements.
Signed visit notes are coded and submitted within 48 hours to minimize revenue cycle delay.
Documentation is reviewed against 2024 AMA E/M guidelines before code assignment, not after denial.
Common Mistakes in Primary Care Billing Services
Applying Pre-2021 E/M Guidelines
The AMA changed office E/M guidelines in 2021, removing the requirement to count examination elements and replacing it with MDM-based level selection. Practices still using the old element-counting methodology are systematically coding visits incorrectly.
Billing AWV as E/M Visit
Medicare Annual Wellness Visits (G0438, G0439) are not the same as E/M visits and use distinct G-codes. Billing an AWV as a standard E/M code (99213-99215) results in denial. Conversely, billing an AWV code when only an E/M was performed results in a misclassification.
Underbilling Chronic Care Management
CCM (99490) requires 20 minutes of clinical staff care management time per month with a documented care plan. Many primary care practices fail to capture and bill CCM monthly for eligible patients, leaving significant recurring revenue uncollected.
Wrong Code for Telehealth E/M
Telehealth office visits use the same E/M codes as in-person visits but require correct place of service coding (02 or 10) and, in some cases, specific modifiers. Missing the telehealth POS or modifier results in payment as an in-person rate instead of the telehealth rate.
How Medsure RCS Manages Primary Care Billing Services
Current E/M Coding Compliance
Office E/M coding using 2024 AMA guidelines with MDM-based level selection and physician time documentation.
Chronic Care Management Billing
Monthly CCM (99490-99491) and complex CCM (99487) billing with care plan documentation and time tracking.
Annual Wellness Visit Billing
Medicare AWV (G0438, G0439) and IPPE (G0402) billing with correct element documentation and same-day E/M coordination.
Preventive Care Coding
Age-banded preventive care codes with correct problem-based E/M pairing when both are performed at the same visit.
Telehealth E/M Billing
Telehealth visit billing with current POS codes, modifiers, and payer-specific telehealth coverage rules.
Transitional Care Management
TCM billing (99495-99496) for patients discharged from hospital or facility within 30 days of the office follow-up visit.
Primary Care Billing Services, Frequently Asked Questions
Since 2021, outpatient office E/M levels are determined by either Medical Decision Making complexity (straightforward, low, moderate, or high) or total physician time on the date of service. The physician chooses the basis that best supports the level, but documentation must clearly reflect whichever basis is selected.
Yes, if during the AWV a significant, separately identifiable medical problem is addressed beyond the AWV scope, an E/M code can be billed with modifier 25. The E/M documentation must clearly distinguish the problem-based visit from the AWV elements.
CCM is a Medicare billing program for patients with two or more chronic conditions expected to last at least 12 months. When a minimum of 20 minutes of clinical staff care management activities (care plan review, coordination, patient contact) are performed per month, code 99490 is billable. It requires patient consent and a documented care plan.
Yes, though billing both on the same day requires careful documentation. In most cases, a same-day hospital discharge and office visit require separate documentation supporting each distinct encounter. We review the documentation to confirm eligibility before billing both services on the same date.
Ask About Primary Care Billing Services
Ready to Improve Your Primary Care Billing Services?
Talk to a Medsure RCS specialist. No commitment, no pressure, just answers.
Sign up for our newsletter to receive updates, industry news, and articles about medical billing and revenue cycle management.